
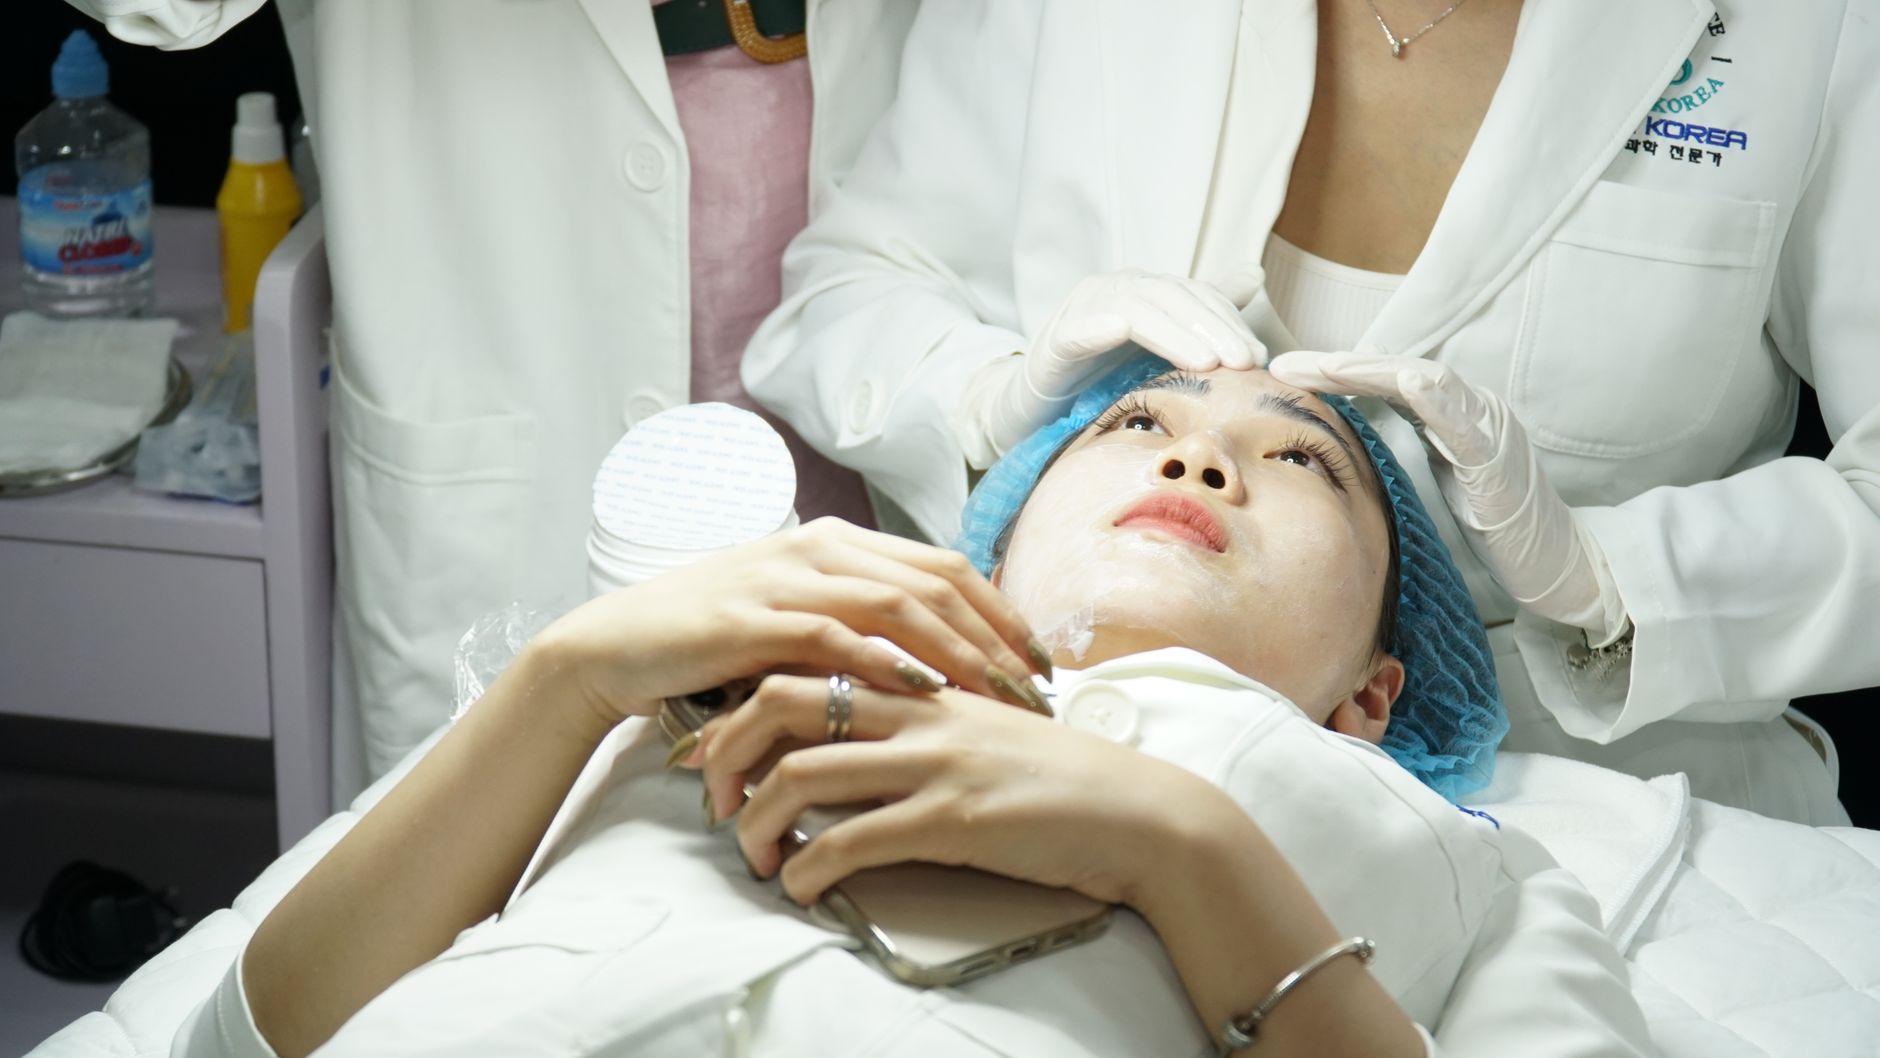
Ask a dermatologist for your exact lesion type and severity grade, your likely triggers, and the best prescription-strength treatment for stubborn whiteheads. Because whiteheads are closed comedones, sealed skin-covered bumps, ask what that sealed structure means for treatment choice and extraction, according to the Cleveland Clinic (Cleveland Clinic whitehead overview). Stubborn means bumps persist despite steady basic care. Bring your product list and a timeline so the visit focuses on decisions.
Medical information disclaimer: This article is for general educational purposes only and does not provide medical advice, diagnosis, or treatment. Always consult a physician or other qualified health professional about symptoms, medications, tests, or treatment decisions.
Table of Contents
- What Type and Severity Do I Have?
- What Could Be Triggering Mine?
- Which First-Line Treatment Fits Me?
- How Long Before We Change Course?
- Do I Need Extraction or Stronger Care?
What Type and Severity Do I Have?
A clinician grades acne by counting spots and checking inflammation, pain, and overall severity to plan treatment. Ask for your exact lesion type and severity grade, according to NHS Inform (NHS Inform acne guide).
Bring notes on where bumps cluster, whether they hurt, and whether they leave marks. Clear grading helps match stubborn closed comedones to the right strength of care.
What Could Be Triggering Mine?
Comedonal acne involves excess sebum, abnormal clumping of skin cells, acne bacteria, and inflammation. Ask about your personal triggers, including hormones, oily products, friction, and medications, according to the Cleveland Clinic (Cleveland Clinic comedonal acne overview).
Bring the facts that reveal patterns. A short checklist makes triggers easier to spot:.
- skin and hair products used daily, including oils and pomades
- friction from helmets, headbands, phones, or picking
- hormone shifts, new prescriptions, and flare timing
Which First-Line Treatment Fits Me?
Topical retinoids including tretinoin, adapalene, tazarotene, and trifarotene are cornerstone first-line therapy for comedonal acne. They unplug comedones and reduce microcomedones, according to the American Academy of Family Physicians summarizing American Academy of Dermatology guidelines (AAFP acne management guidelines summary).
Ask which retinoid suits your skin, how to start it, and how to handle dryness or irritation. According to the National Institute of Arthritis and Musculoskeletal and Skin Diseases, benzoyl peroxide, salicylic acid, sulfur, and resorcinol also help break down whiteheads and blackheads, with salicylic acid reducing shedding of follicle-lining cells.
How Long Before We Change Course?
Acne treatment can take several months to improve. According to NHS 111 Wales, ask what response time to expect, when to return, and what criteria would prompt a change in prescription treatment.
Track progress with photos, bump counts, and notes on pain or scarring. Ask what counts as improvement and what should trigger a sooner call.
Do I Need Extraction or Stronger Care?
Do not squeeze or pop whiteheads because it can damage skin and cause scarring. According to the American Academy of Dermatology, ask whether you need in-office comedo extraction, stronger topicals, or referral to a dermatologist instead.
Seek stronger care when lesions persist, hurt, spread widely, or scar. Stop picking and book follow-up if bumps spread, hurt, or leave marks.